On Tuesday October 13 2026 the Australasian College for Emergency Medicine (ACEM) released a report revealing Australia’s health system is not prepared for the growing number of older patients arriving in emergency departments (EDs).
- 53,510 older people spent longer than 24 hours in an ED awaiting a bed in 2023-24, almost 40,000 more than in 2018-19 (15,084)
- Only half (54 per cent) of older patients needing admission left the ED within the eight-hour target, compared to almost three-quarters (71 per cent) of younger patients — and that gap has widened sharply since 2018-19
- A projected 411 per cent increase in ED arrivals for those aged 85 and over by 2050
- Strengthen alternative pathways to acute medical care for older people to reduce ED demand and hospital admissions.
Recommendations for the Federal Government
- Jointly invest with State and Territory Governments in programs that strengthen integration between hospitals, aged care, community services, Aboriginal Community Controlled Health Organisations, and other support services, including transitional and step-down care, to support early discharge of older patients.
- Jointly invest with State and Territory Governments in additional emergency medicine telehealth support for residential aged care staff and community care services.
- Fund targeted, culturally safe alternative care pathways and outreach programs for Aboriginal and Torres Strait Islander Elders and Older People, co-designed with Aboriginal Community Controlled Health Organisations, to address the disproportionate rise in ED presentations.
Recommendations for State and Territory Governments
- Provide hospitals with adequate funding to deliver and sustain in-reach medical and multidisciplinary services to older people in residential aged care and in the community.
- Provide funding for additional Hospital-in-the-Home places to provide alternatives to hospitalisation and support early discharge for older patients.
- Jointly invest with the Federal Government in additional Hospital to Aged Care Dementia Support Program (HACDSP) places, to support people with dementia in their transition from hospital either back home with appropriate support or into residential aged care.
- Jointly invest with the Federal Government in additional Transition Care Program places and strengthen integration between hospitals, aged care, community services and other support services, particularly for people living with complex conditions, dementia or behavioural symptoms.
Recommendations for hospitals
- Expand and adequately fund geriatric-focused outreach emergency and geriatric programs providing acute assessment and in-home care.
2. Improve patient flow through the ED and reduce access block.
Recommendations for the Federal Government
- Require State and Territory Governments to adopt and report on ACEM’s Hospital Access Targets (HAT) to ensure uniform, visible data across jurisdictions.
- Increase Federal Government hospital funding to match State and Territory Government funding in a 50/50 cost-sharing arrangement.
- Commit to ongoing funding for the Emergency Medicine Education and Training (EMET) program to better equip smaller rural and remote EDs to treat older patients locally, reducing inter-hospital transfers and delivering care closer to home.
- Improve how My Health Record, My Aged Care and hospital IT systems connect, so information can be shared easily between services.
- Implement digital platforms that allow visibility of advance care directives across healthcare settings.
Recommendations for State and Territory Governments
- Adequately fund an increase in inpatient bed capacity with demographics-informed planning.
- Adequately fund care coordination services, including culturally appropriate care, for older people with complex health conditions who are hospitalised to assist in discharge planning and linking to other health services.
- Fund hospital security, staff safety training and environmental design upgrades in EDs to reduce the risk of violence associated with overcrowding and extended wait times.
Recommendations for hospitals
- Implement a whole-of-hospital approach to reduce ED length of stay for older people, with shared accountability for patient flow and inpatient bed access across the hospital.
- Increase funding allocation for ED medical staffing to comply with ACEM staffing guidelines outlined in Constructing a sustainable emergency department medical workforce.1
- Expand and adequately resource geriatric-focused ED programs to optimise care for older people and avoid unnecessary hospital admissions.
- Implement violence prevention and staff safety measures in EDs, informed by the recommendations of ACEM’s Breaking Point: An Urgent Call to Action on Emergency Department Safety report, to address the rising levels of violence linked to overcrowding and access block.
3. Expand prevention mechanisms to reduce ED attendance and hospitalisation through early intervention.
Recommendations for the Federal Government
- Rapidly expand and adequately resource the residential aged care sector to meet growing demand and complexity, delivering at least 10,000 additional beds per year by 2028.
- Increase funding to residential aged care providers to support the 24/7 registered nurse coverage mandated from July 2023.
- Improve targeted incentives to encourage residential aged care providers to admit residents living with complex conditions, dementia or behavioural symptoms and increase funding for additional Specialist Dementia Units.
- Improve the adequacy, responsiveness and clinical capacity of Support at Home and Commonwealth Home Support Program services to reduce preventable ED presentations and hospital admissions, including introducing maximum wait time standards for each Support at Home Priority System category.
- In collaboration with State and Territory Governments, deliver improved pathways and assistance to navigate and access primary, community and aged care services, including expanding the Aged Care Navigator program as recommended in the Royal Commission into Aged Care Quality and Safety.
- Fund sustainable primary care models, including adequate remuneration for general practitioners (GPs) to provide longitudinal, responsive care for older people, especially those living with complex conditions.
- Redesign the General Practice in Aged Care Incentive (GPACI) program to provide for equitable increases in incentives for all GP practices to provide services within residential aged care.
- Meet the National Preventive Health Strategy’s commitment to increase preventive health spending to 5 per cent of the health budget by 2030.
Recommendations for State and Territory Governments
- Incentivise aged care providers to increase their capacity through State and Territory Government levers such as low-interest loans and planning assistance.
- Fund and facilitate a concerted public health campaign focusing on healthy ageing and preventive health.
- Invest greater resources into State and Territory Government health promotion services, including community-based programs that support healthy ageing.
4. Fund research into models of primary and acute care to improve outcomes for older people.
Recommendations for the Federal Government
- Establish and fund a National Emergency Medicine Research Foundation to support dedicated, long-term research into emergency medicine and acute care for all patients, including older people.
- Allocate regular targeted funding rounds for emergency medicine research from the Medical Research Futures Fund including research into models of care that improve outcomes for older people requiring acute care.
- Require State and Territory Governments to report age-disaggregated data on all key quality and performance indicators, including length of stay, access block, and exit block.
- Develop and validate health outcome measures for older people that clearly show performance and equity in the delivery of quality care across the acute care system.
- Require the collection and public reporting of ED length of stay, access block and treatment completion data disaggregated by Aboriginal and Torres Strait Islander status, to monitor and address the disproportionate harm experienced by older First Nations people in EDs.
Recommendations for State and Territory Governments
- Implement age-disaggregated data collection for all key quality and performance indicators monitored by hospitals to support improved visibility and care outcomes for older people.
- Collaborate with the Federal Government in developing data systems that improve visibility of extended ED length of stay, access block and exit block.
- Support clinicians to undertake research into models of care that aim to improve health outcomes of older people and reduce ED length of stay and hospitalisations.

NSW steps further into aged care as report warns state not to replace Commonwealth
On Wednesday 14 October 2026 the Minister for Health announced the NSW Government will provide interim aged care services to help older stranded patients to return from hospital to the comfort of home more quickly and safely.
The announcement was made the same day a new report by the NSW Productivity and Equality Commission (PEC) warned any state action needs to complement, not replace, the Commonwealth’s responsibility for aged care.
PEC report: 7,000 stranded older patients within 10 years
In May 2026, the NSW Productivity and Equality Commission was requested by the NSW Minister for Health to review policy, regulatory and system levers to address the delayed discharge of older patients from NSW public hospitals.
The NSW Government commissioned the PEC’s Helping older patients stranded in NSW public hospitals report in response to the growing impact discharge delays are having on older people, their families, and hospitals across NSW.
The Review was guided by four principles:
- People should receive care in the setting best suited to their needs.
- Governments should focus on areas within their responsibility and control.
- Actions should improve outcomes, efficiency, equity and public value.
- Governments should work together while maintaining clear accountability
The Commissioner provided the Review’s final report to the Minister on 14 October 2026. The report found that current funding and policy settings have not supported sufficient aged care supply to keep pace with demand, resulting in a growing number of older stranded patients. It estimates the fiscal, economic, and wellbeing costs associated with older people being stranded in NSW hospitals exceed $1 billion annually.
Based on Commission modelling, the number of older stranded patients could increase from around 1,100 today to more than 7,000 by 2036 as the population ages and demand for aged care continues to outpace supply.
The Report states:
'During the 2025 intergovernmental negotiations on health funding, concerns were raised that state planning barriers were constraining residential aged care supply. The Commission has therefore examined the extent to which NSW planning settings may be contributing to the shortage of aged care beds.
The NSW planning system plays an important role in determining where and how many aged care beds can be supplied in NSW. It enables aged care homes to be built close to hospitals, families, and other supports that older people rely on, while balancing impacts on surrounding communities.
In practice, planning controls such as zoning and height limits can affect whether aged care developments could be large enough to operate at an efficient scale and compete for scarce land with other developments, such as residential apartments. While recent NSW planning changes have made it easier to develop new aged care homes, other jurisdictions are providing further planning support to allow aged care developments to achieve an efficient scale. Overall, however, the evidence does not suggest that planning is the main factor limiting aged care supply in NSW.
NSW adopting planning changes similar to those made in other jurisdictions could support an additional 164 aged care beds each year. This is only around 6% of the roughly 2,600 additional beds NSW needs each year. Accordingly, while planning changes can help, resolving the projected aged care shortage will depend fundamentally on improvements to Australian Government funding settings.'
The Report found funding gaps reduce the feasibility of supporting low-means and high-needs residents:
'Providers note that AN-ACC funding does not adequately reflect current costs. As it is based on indexed historical cost data, funding adjustments lag periods of rapid wage and price growth. The 2.6% increase in base AN-ACC funding announced in September 2026 was below both consumer price inflation (3.5% in the 12 months to June 2026) and aged care award wage growth (4.75% from 1 July 2026). As one provider noted:
It's a funding cut in real terms, which translates to $300k less than expected for our FY27 operations, and reduces valuation of the new project now under construction (and any future projects), so it directly weakens the already shaky case for investment in the sector. - Harbison Care
Further recording:
'The Australian Government’s AN-ACC funding model is intended to align funding with residents’ care needs. However, consultation suggests that current funding arrangements do not adequately compensate providers for caring for residents with limited financial means or complex care needs.
Providers identified these groups as being disproportionately represented among stranded patients. As one provider noted:
Stranded patients are disproportionately those unable to self-fund and/or with very high care needs, which limits providers’ capacity to take them on, particularly where supply is already constrained.
These funding challenges are amplified by high occupancy rates. As discussed in section 3.1.3, residential aged care occupancy remains close to historic highs. Current supply constraints and funding settings require facilities to operate at near-full occupancy to remain financially viable.
As one provider noted:
… lack of supply is the key problem because the funding model requires structurally full occupancy to break even. - Harbison Care
In an environment of constrained supply and excess demand, providers can be selective about admissions. As noted by former Inspector-General of Aged Care Natalie Siegel-Brown, providers can ‘cherry pick’ residents when demand exceeds available beds.
While some providers are willing to admit more low-means and high-needs residents, funding arrangements often do not adequately cover the costs of providing care. This creates a financial disincentive to provide residential aged care to those having the greatest need for support.'
...
Several providers reported that accommodation funding for low-means residents remains insufficient. This finding is consistent with the Australian Government's Accommodation Review, which concluded that ‘funding for supported residents has not kept pace with rising construction and accommodation costs.’
In response, the Australian Government’s 2026-27 reforms materially improved accommodation funding by including a new $30 per day capital supplement. As discussed in section 4.1.2, these changes significantly improved development feasibility and narrowed the funding gap between low-means and self-funded residents.
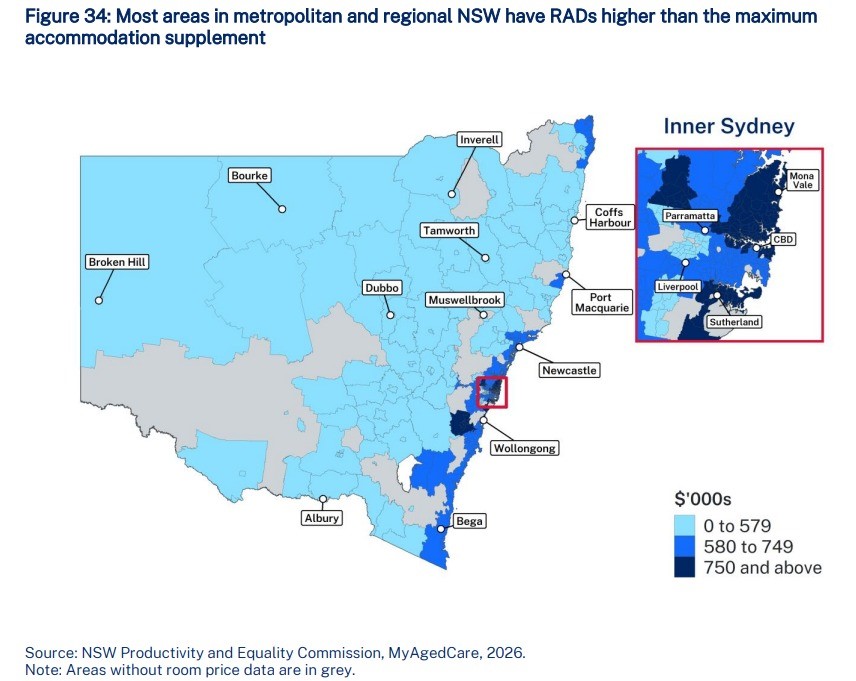
However, providers reported that material funding gaps remain, particularly in higher-cost metropolitan markets. Accommodation revenue from low-means residents can remain substantially below that generated by self-funded residents, especially when room prices exceed $580,000 (see figure 33). As room prices increase, so does the revenue gap, strengthening incentives to favour self-funded residents over low-means residents.
Several providers also noted that achieving the highest accommodation supplement can be challenging because eligibility depends on maintaining a high proportion of low-means residents. This can create financial pressure during the establishment phase of new facilities. In addition, self-funded residents remain attractive because refundable accommodation deposits (RADs) provide a valuable source of capital that can reduce debt requirements and fund future investment.
Overall, recent reforms have reduced, but not removed, incentives to favour wealthy self-funded residents over poorer, low-means residents.
Several providers reported that new residential aged care developments are increasingly concentrated in areas where residents can afford higher accommodation prices and larger RADs.
In metropolitan NSW, a quarter of areas have median advertised room prices above $750,000 (figure 34).
Our modelling suggests that higher room prices substantially improve development feasibility. Increasing room prices to at least $750,000 reduces the average feasibility gap in metropolitan NSW from $59,300 per bed to $13,000 per bed, while increasing the share of feasible locations from around 45% to 64%. Residents with capacity to pay can outweigh higher land and development costs, making investment more attractive in wealthier communities. New aged care homes built in wealthier communities can still improve access across the wider aged care system by freeing up beds in existing homes. However, providers noted that higher accommodation deposits alone are not enough to address challenges with feasibility. Suitable sites remain scarce, developers face competition from higher value land uses, and many regional communities cannot support large accommodation payments. Moreover, without adequate funding for low-means residents, there is a risk that future developments become increasingly concentrated in wealthier areas rather than in the communities with the greatest need.'
The PEC recommends the Commonwealth Government increase funding for aged care, separate to funding for healthcare and hospital activity.
The Commission recommended a range of reforms aimed at reducing patient stranding and improving outcomes for older people, including:
- increasing Australian Government funding to make sure aged care supply can keep up with demand
- creating a separate funding and accountability system for stranded patients, rather than treating them as routine hospital patients
- improving statewide reporting on stranded patient numbers and causes of delay
- ensuring older people can access Support at Home and other community-based services as soon as they need them
- strengthening hospital discharge planning and coordination to help patients leave hospital sooner
- expanding intermediate care services that provide alternatives to prolonged hospital stays
- evaluating and expanding interventions that reduce dementia risk and help people living with dementia remain independent for longer.
NSW Government's interim aged care services
The NSW Government will establish a new $28 million pilot program to provide interim aged care services to assist older patients waiting to be discharged from hospital to return home, while they wait for Commonwealth Government Support At Home packages.
The support may include clinical care such as wound care and symptom management, personal care, domestic assistance, assistive technology, and home modifications.
'The $28 million pilot program will assist more than 300 patients each year, and unlock more hospital beds for patients who need them the most.' the government said in a released statement
'This forms part of the Minns Labor Government’s $35.7 million Aged Care Response Package, to help older patients stay healthy and avoid hospital, as well as to help older patients return home more quickly and safely.'
NSW Government unlocking beds
The NSW Government states it has consistently pursued reform through avenues available to it to alleviate the impact stranded patients have on the people concerned and the healthcare system more broadly, including:
- Expanding the capability of our specialist geriatric care services, providing hospital-level care to more than 39,000 older patients across the state, in the comfort of their own home and without the stress of a traditional hospital stay.
- Strengthening discharge planning and to support older people to transition well from hospital to aged care despite the challenges arising from Commonwealth stranded patients, there have been improvements in emergency department performance and the number of people accessing care outside of the hospital.
'The NSW Government will also continue to work constructively with the Commonwealth Government and all states and territories through the Hospital Discharge Joint Taskforce and Health Ministers Meeting, recognising this challenge goes past state boundaries and requires collective national action.' the government said
NSW Minister for Health, the Hon. Ryan Park, stated:
“I would like to thank the NSW Productivity and Equality Commissioner, Peter Achterstraat AM, and the broader Commission team for the significant work undertaken over the past year to examine this issue and deliver a comprehensive, high-quality report.
“The Commonwealth Government is responsible for the provision of aged care and NDIS placements, yet this report shows that this duty is not being met and thousands of hospital beds will be lost as a result.
“The report also warns that any state action needs to complement, not replace, the Commonwealth’s responsibility for aged care.
“We cannot continue to wait for the Commonwealth Government to deliver on its aged care responsibilities because too many people are already stranded in our hospitals and they deserve better.
“That’s why today we are announcing the Minns Labor Government will provide interim aged care services to help older stranded patients return from hospital to the comfort of home more quickly and safely, as part of a broader effort to get people the care they need and deserve, while unlocking hospital beds for those who need them the most.”
The report concludes that while NSW should pursue reforms within its control, sustained reductions in stranded patients will only be possible if the Australian Government ensures residential and home-based aged care capacity keeps pace with the needs of an ageing population.
The NSW Productivity and Equality Commission's report Helping older patients stranded in NSW public hospitals is available to download at: (PDF 5.55MB)
Peter Achterstraat AM, NSW Productivity and Equality Commissioner, stated:
"Older people should receive care in the setting that best meets their needs. For stranded patients, that is no longer a hospital bed.
"Older stranded patients are the canary in the coalmine. Their growing presence in NSW hospitals signals that pressures across the health and aged care systems are reaching a critical point.
"More than half of older stranded patients are waiting for residential aged care. They remain in hospital not because they need hospital care, but because the aged care services they need are unavailable.
"We estimate the costs associated with older stranded patients exceed $1 billion each year, while reducing the effective capacity of hospitals across NSW.
"Without action, the number of older stranded patients could increase from around 1,100 today to more than 7,000 within the next 10 years.
"This is not simply a hospital problem. NSW hospitals are carrying the consequences of insufficient aged care capacity elsewhere in the care system.
"The biggest long-term opportunity to reduce stranded patients is for the Australian Government to ensure aged care and home care capacity grows in line with Australia's ageing population.
"NSW should act on every lever within its control. However, sustained improvements will require aged care capacity to expand in line with Australia's ageing population.”